For many people with Indian skin tones, melasma starts quietly. It often appears as a faint, shadowy mark across the cheekbones, bridge of the nose, forehead, or upper lip. Many people mistake these patches for a stubborn suntan or dark marks left behind by acne. Over time, the patches grow darker and spread. When searching for effective melasma treatment for Indian skin, many people turn to store-bought brightening creams, rough face scrubs, or foaming cleansers. Sadly, these surface products rarely clear the pigment and can even make the discoloration worse.
Melanin-rich skin reacts very quickly to heat, friction, and light. When skin experiences physical trauma or strong inflammation, pigment-making cells become overactive (Comparative efficacy of chemical peels and laser treatments in mela…). In skin of color (Fitzpatrick types III to VI), clinical procedures like laser treatments carry an elevated risk of post-inflammatory hyperpigmentation (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Doctors must use great care when treating darker skin so they do not replace melasma with new dark marks (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Harsh home scrubs or strong, unguided formulas can also irritate the skin barrier and cause rebound darkening.
Managing melasma on Indian skin requires patience and medical guidance. Quick fixes often backfire on deeper skin tones. Safe pigment care focuses on calming active melanocytes, protecting the skin barrier, and using gentle clinical steps planned by an experienced dermatologist.
Understanding Melasma Depth: Epidermal, Dermal, and Mixed Pigment
Over-the-counter creams often fail because melasma rarely stays on the surface of the skin. Under the microscope, melasma shows pigment located in the epidermal layer or extending into the dermis (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Knowing where the pigment sits helps determine what treatments can achieve (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Dermatologists group melasma by how deep the melanin lies.
- Epidermal Melasma: Excess pigment sits in the basal and suprabasal layers of the epidermis, where melanocytes have prominent branches (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Under a Wood's lamp, this surface pigment enhances clearly (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Because melanocytes sit mainly in the epidermis, histological studies confirm that topical treatments help clear epidermal melasma (A Scoping Review on Melasma Treatments and Their Histopathologic Co…).
- Dermal Melasma: Melanin and pigment-carrying cells, called melanophages, sit in the upper and middle dermis, and sometimes reach the deeper dermis (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Dermal melasma shows little to no enhancement under a Wood's lamp (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). On the face, dermal pigment often looks like a soft, bluish-gray or slate-brown shadow with hazy edges.
- Mixed Pigment Presentations: In clinical practice, many individuals display pigment across both the surface and deeper skin layers. Dermal melasma itself often features pigment in both the epidermis and the dermis (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Treating mixed pigment requires clearing surface melanin while calming deeper cells without triggering new irritation.
This difference in depth explains why cosmetic creams rarely clear dark patches on their own. Topical retinoids and hydroquinone can reduce surface pigment and lower the number of active melanocytes (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Yet, research shows they do not clear deep dermal melanophages (A Scoping Review on Melasma Treatments and Their Histopathologic Co…).
In the same way, green light lasers use shorter wavelengths that do not penetrate deeply into the skin (Lasers for Treatment of Melasma and Post-Inflammatory Hyperpigmenta…). As a result, they work only on epidermal melasma (Lasers for Treatment of Melasma and Post-Inflammatory Hyperpigmenta…). Understanding pigment depth protects patients from spending time and money on surface creams that cannot reach deep melanin deposits.
The Rebound Danger: Bleaching Creams, Steroid Abuse, and Ochronosis
Frustrated by stubborn patches, many people buy unverified pharmacy creams. Medical guidelines state that topical therapies are the main medical step for melasma, but self-treating with steroid creams must be strictly avoided (Medical Management of Melasma: A Review with Consensus Recommendati…, Melasma: Causes, Symptoms and Care Tips). Applying unmonitored bleaching formulas can cause severe skin complications.
Studies of Indian patients who used mometasone-based triple combination creams without medical supervision found frequent side effects (Medical Management of Melasma: A Review with Consensus Recommendati…). Common steroid-related harms included skin thinning, enlarged visible blood vessels, excess facial hair, and acne breakouts (Medical Management of Melasma: A Review with Consensus Recommendati…). In addition, one-third of the patients reported that their dark patches worsened after using these creams (Medical Management of Melasma: A Review with Consensus Recommendati…). For this reason, dermatologists strongly warn against self-medicating with combination steroid creams (Melasma: Causes, Symptoms and Care Tips).
Using hydroquinone in concentrations higher than 5% for long periods brings serious dangers. It increases skin irritation and can cause a condition called exogenous ochronosis (Medical Management of Melasma: A Review with Consensus Recommendati…). Long-term, unmonitored use of hydroquinone or modified Kligman's formula can lead to speckled darkening, confetti-like loss of color, and tiny dark brown bumps on the cheeks (Dermoscopic criteria for differentiating exogenous ochronosis from…).
Under a microscope, ochronosis shows short, stout, banana-shaped, ochre-colored fibers in the dermis (Dermoscopic criteria for differentiating exogenous ochronosis from…). When ochronosis begins, patients often think their melasma is simply returning (Dermoscopic criteria for differentiating exogenous ochronosis from…). They apply more bleaching cream, which makes the damage worse (Dermoscopic criteria for differentiating exogenous ochronosis from…). A dermatologist uses dermoscopy to tell the two conditions apart. Regular melasma accents the normal net-like pigment pattern of the skin (Dermoscopic criteria for differentiating exogenous ochronosis from…). In contrast, ochronosis displays dark brown dots and worm-like shapes that cover up hair follicle openings (Dermoscopic criteria for differentiating exogenous ochronosis from…). Spotting these signs early helps prevent long-lasting, severe discoloration.
In-Clinic Melasma Treatment for Indian Skin: Balancing Peels and Laser Toning
When melasma does not clear with daily topicals, dermatologists may consider in-clinic procedures (Medical Management of Melasma: A Review with Consensus Recommendati…). However, procedural treatments require extra caution in darker skin types to avoid trading melasma for post-inflammatory dark marks (A Scoping Review on Melasma Treatments and Their Histopathologic Co…).
Expert guidelines from the South Asian Pigmentary Forum and the Pigmentary Disorders Society note that topical therapies must always be first-line care (Medical Management of Melasma: A Review with Consensus Recommendati…). Chemical peels serve as second-line options, while lasers are kept strictly as third-line choices (Medical Management of Melasma: A Review with Consensus Recommendati…). A meta-analysis showed that while lasers reduced melasma severity scores more than chemical peels, peels had a notably safer complication profile with fewer adverse events (Comparative efficacy of chemical peels and laser treatments in mela…). In fact, studies show that up to 25% of patients treated with Q-switched lasers develop post-inflammatory hyperpigmentation, and darker skin types face this problem most often (Comparative efficacy of chemical peels and laser treatments in mela…).
Why do lasers cause rebound marks on Indian skin? Laser heat or injury can damage the basal cell layer, allowing melanophages to gather in the upper dermis (Lasers for Treatment of Melasma and Post-Inflammatory Hyperpigmenta…). Skin inflammation also releases chemicals like arachidonic acid, prostaglandins, and leukotrienes (Lasers for Treatment of Melasma and Post-Inflammatory Hyperpigmenta…). These chemicals tell melanocytes to produce extra melanin (Lasers for Treatment of Melasma and Post-Inflammatory Hyperpigmenta…). Because high energy fluences cause post-inflammatory dark marks in darker skin tones, dermatologists use lower fluences when performing laser toning on skin of color (Lasers for Treatment of Melasma and Post-Inflammatory Hyperpigmenta…).
When using chemical peels, superficial options like glycolic acid or lactic acid are reserved for resistant cases (Melasma: Causes, Symptoms and Care Tips). Deeper peels remove more pigment, but they carry high risks of scarring and lasting redness in skin of color (Comparative efficacy of chemical peels and laser treatments in mela…). In addition, microneedling has shown useful histological results in melasma care (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Studies show that microneedling repairs basement membrane damage, lowers pendulous melanocytes, and helps clear dermal melanophages (A Scoping Review on Melasma Treatments and Their Histopathologic Co…).
Navigating Melasma Triggers Alongside Other Aesthetic Treatments
Melasma is driven by internal and external triggers that stimulate pigment cells. Research shows that melasma patches often involve blood vessel changes and higher mast cell counts (A Scoping Review on Melasma Treatments and Their Histopathologic Co…, Oral Tranexamic Acid for the Treatment of Melasma: Evidence and Exp…). Studies also reveal basement membrane damage beneath the pigment (A Scoping Review on Melasma Treatments and Their Histopathologic Co…). Ultraviolet light, hormones, and cell injury can all activate melanocyte pathways in the skin (Oral Tranexamic Acid for the Treatment of Melasma: Evidence and Exp…). Hormonal shifts, such as those that happen during pregnancy, frequently cause melasma to flare (Melasma: Causes, Symptoms and Care Tips).
Because melanin-rich skin with melasma reacts strongly to inflammation, patients must coordinate their aesthetic procedures carefully. If you are planning laser hair removal, acne treatment, or acne scar treatment, tell your dermatologist about your melasma beforehand.
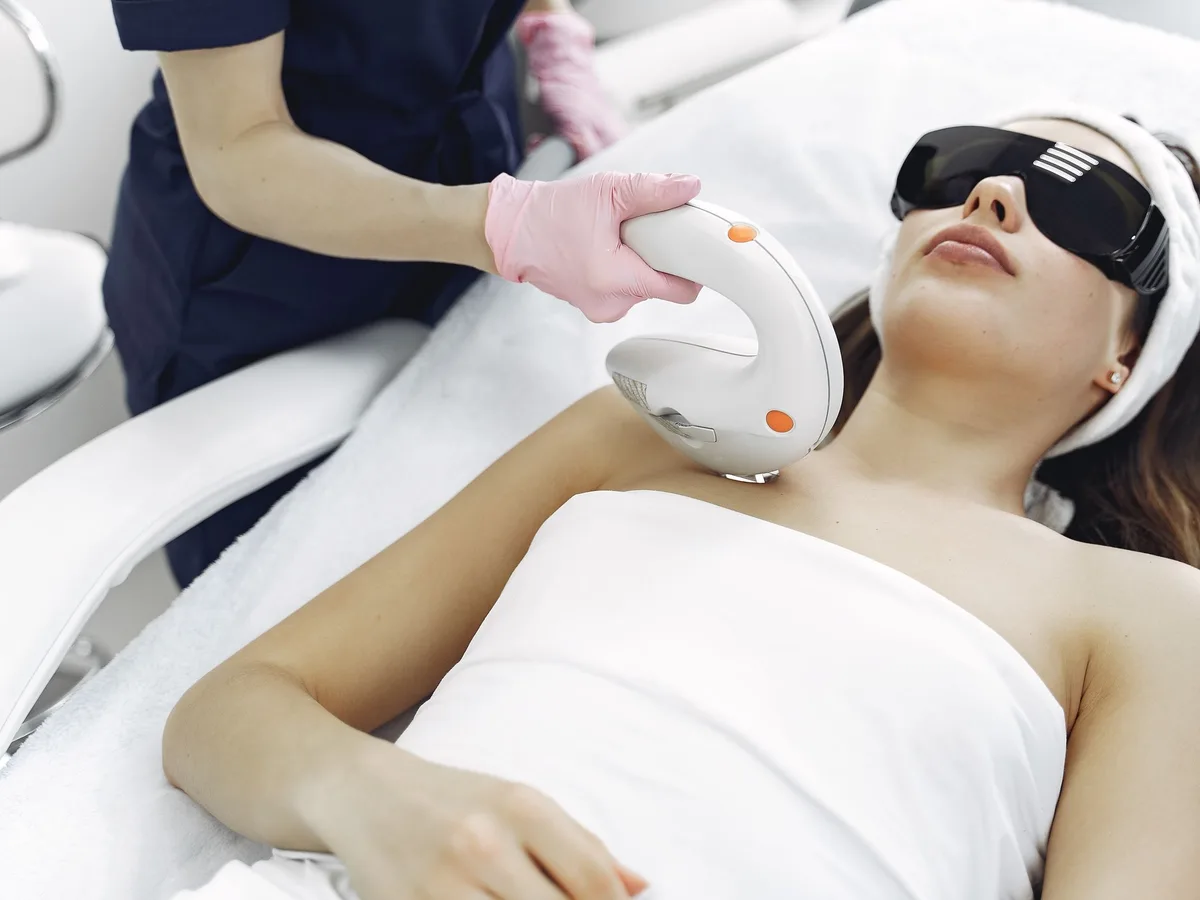
- Laser Hair Removal: Laser hair reduction targets melanin inside hair roots using optical energy. If laser pulses pass over active melasma without adjusted settings, heat can leak into surrounding skin. This heat can trigger reactive melanocytes and cause melasma to flare. Pulse widths, wavelengths, and contact cooling must be customized for Indian skin tones to protect surface melanocytes.
- Acne Treatment: Active acne pimples cause swelling and redness that quickly lead to dark spots in Indian skin. Using strong scrubs or unbuffered acid washes can damage the skin barrier. This irritation worsens both post-acne marks and active melasma. Dermatologists recommend gentle, anti-inflammatory acne care that clears blemishes while protecting the skin barrier.
- Acne Scar Treatment: Scar procedures like subcision, microneedling, or fractional lasers prompt collagen remodeling. If a patient has active melasma, intense procedural heat can cause new dark patches. Dermatologists often calm and stabilize active melasma first before beginning targeted scar revisions.
Beyond Standard SPF: The Critical Role of Visible Light and Iron Oxides
Sun protection is essential for anyone dealing with melasma. Dermatologists advise year-round, life-long sun protection using broad-spectrum sunscreen with an SPF of 50 or higher applied to the whole face every day (Melasma: Causes, Symptoms and Care Tips). Yet, many standard sun routines fail to prevent pigment from returning.
Most people choose untinted sunscreens designed to block ultraviolet A and ultraviolet B rays. However, ultraviolet light is not the only trigger. Visible light, which covers wavelengths from 400 to 700 nanometers, makes up about 45% of the solar spectrum (Photoprotection Efficacy of Sun Protection Factor and Iron Oxide Fo…). In darker skin, visible light causes both fast and long-lasting skin darkening, worsening facial dyschromia (Photoprotection Efficacy of Sun Protection Factor and Iron Oxide Fo…). Broad-spectrum SPF 50+ sunscreen alone cannot protect the skin from visible light-induced pigmentation (Photoprotection Efficacy of Sun Protection Factor and Iron Oxide Fo…).
To block visible light, sunscreens must contain iron oxides, which absorb these visible rays (Medical Management of Melasma: A Review with Consensus Recommendati…, Photoprotection Efficacy of Sun Protection Factor and Iron Oxide Fo…). Research shows that sunscreens with iron oxides protect Fitzpatrick type IV skin from visible light pigmentation, while untinted SPF 50+ sunscreens cannot (Photoprotection Efficacy of Sun Protection Factor and Iron Oxide Fo…). In a 12-week study, 36% of melasma patients who used SPF 50 with iron oxides had superior improvements in skin radiance compared to 0% of those using standard SPF 50 alone (Photoprotection Efficacy of Sun Protection Factor and Iron Oxide Fo…). Adding iron oxides also lowers melasma relapse rates (Medical Management of Melasma: A Review with Consensus Recommendati…).
Daily habits make all the difference. Apply a broad-spectrum SPF 50+ sunscreen every morning (Melasma: Causes, Symptoms and Care Tips). When spending time outdoors in the summer, reapply your sunscreen every two hours to keep your skin shielded (Melasma: Causes, Symptoms and Care Tips). Pairing daily sunscreen with wide-brimmed hats and avoiding excess kitchen heat helps keep pigment stable.
Building a Sustainable, Dermatologist-Led Melasma Care Plan
Managing melasma on Indian skin requires consistency, time, and gentle care. Because melanocytes remain sensitive to heat, light, and hormones, melasma cannot be solved with aggressive quick fixes. Long-term pigment control relies on setting honest expectations, protecting the skin barrier, using tinted photoprotection, and following medical advice.
At Skin Essence in Kalyani Nagar, Pune, melasma care is guided by Dr. Daksha Patel, MBBS, MD (Skin & VD), an experienced dermatologist and cosmetologist. Every treatment plan is planned around the patient's skin type, pigment depth, and goals rather than chosen from a fixed chart. Whether care involves medical topicals, superficial chemical peels, or low-fluence laser toning, each step is chosen carefully to avoid post-inflammatory rebound.
If you are struggling with dark facial patches, avoid self-medicating with unverified pharmacy creams. Scheduling a consultation with an MD dermatologist at Skin Essence in Kalyani Nagar, Pune gives you a clear diagnosis and a safe, personalized path toward calm, healthy skin.
Frequently asked questions
Why do over-the-counter creams often fail to treat melasma on Indian skin?
Melasma often extends into the deeper dermis, where pigment sits inside melanophages. Topical retinoids and hydroquinone can reduce surface epidermal melanin, but research shows they do not clear deep dermal pigment deposits.
What are the risks of using steroid creams or high-strength hydroquinone without supervision?
Unmonitored use of triple-combination steroid creams can cause skin thinning, visible blood vessels, acne breakouts, and rebound darkening. Long-term hydroquinone use above 5% can trigger exogenous ochronosis, leading to speckled dark marks and permanent discoloration.
Are lasers safe for melasma on Indian skin tones?
Lasers carry an elevated risk of post-inflammatory hyperpigmentation on darker skin types, affecting up to 25% of patients treated with Q-switched lasers. When used, dermatologists keep them as third-line options and use low fluences to avoid triggering reactive melanocytes.
Why is regular untinted sunscreen not enough for melasma?
Standard broad-spectrum SPF 50+ sunscreens shield against ultraviolet rays but fail to block visible light, which triggers long-lasting darkening in skin of color. Sunscreens containing iron oxides absorb visible light, offering superior protection and reducing relapse rates.